Symptoms and imaging
Evaluation focuses on symptomatic fibroids, their location and size, and whether they explain the bleeding or pressure. A scan alone is not enough to select treatment.
Los Angeles & Orange County · UFE care
Understand a uterus-preserving option for symptomatic fibroids. Explore bleeding and pressure symptoms, recovery, treatment alternatives and pregnancy questions.
Van Nuys · Tarzana · Fountain Valley
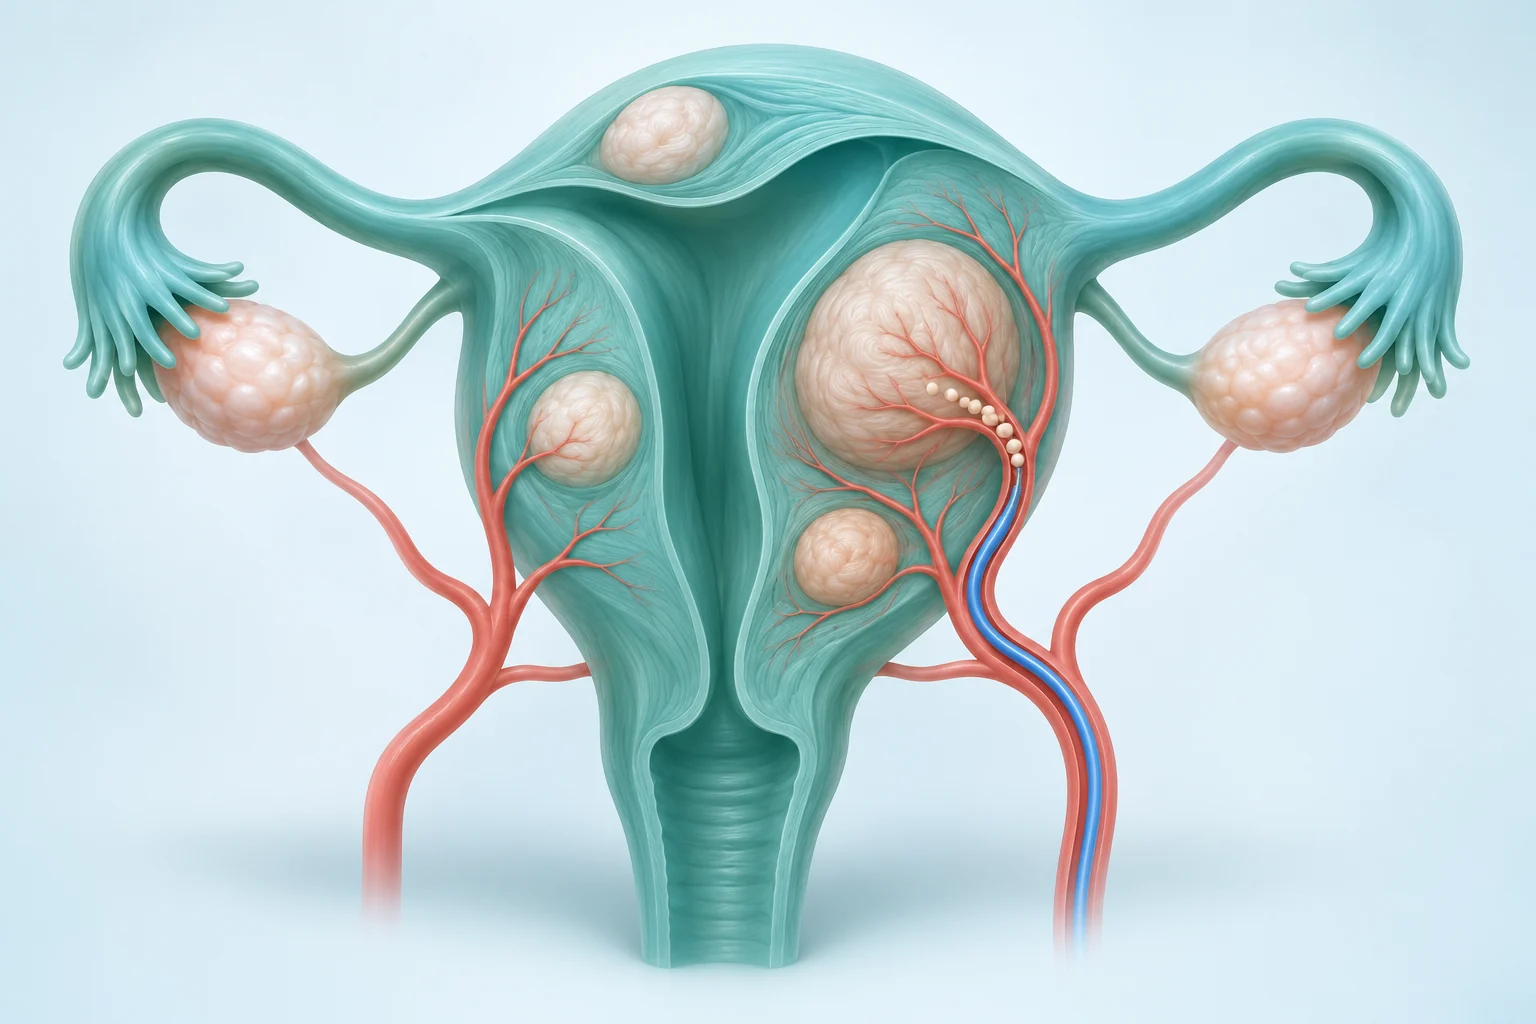
If your imaging also mentions adenomyosis, read how fibroids and adenomyosis differ before comparing treatments.
How does UFE treat fibroids? UFE, also called uterine artery embolization (UAE), reduces blood flow to fibroids through an arterial catheter. Treated fibroids can shrink and symptoms may improve over time. It keeps the uterus in place, but it does not surgically remove fibroids and does not guarantee preserved fertility.
Fibroids can cause heavy or prolonged menstrual bleeding, pelvic pressure, urinary frequency, abdominal fullness and other symptoms. Anemia from bleeding may need treatment alongside fibroid evaluation. Fibroids found on a scan do not always explain every symptom.
Your clinician reviews ultrasound or MRI findings, bleeding history and other possible causes. Gynecologic testing may be needed before deciding on embolization. ACOG’s fibroid overview explains diagnosis and the range of treatments.
Compare all major fibroid treatment options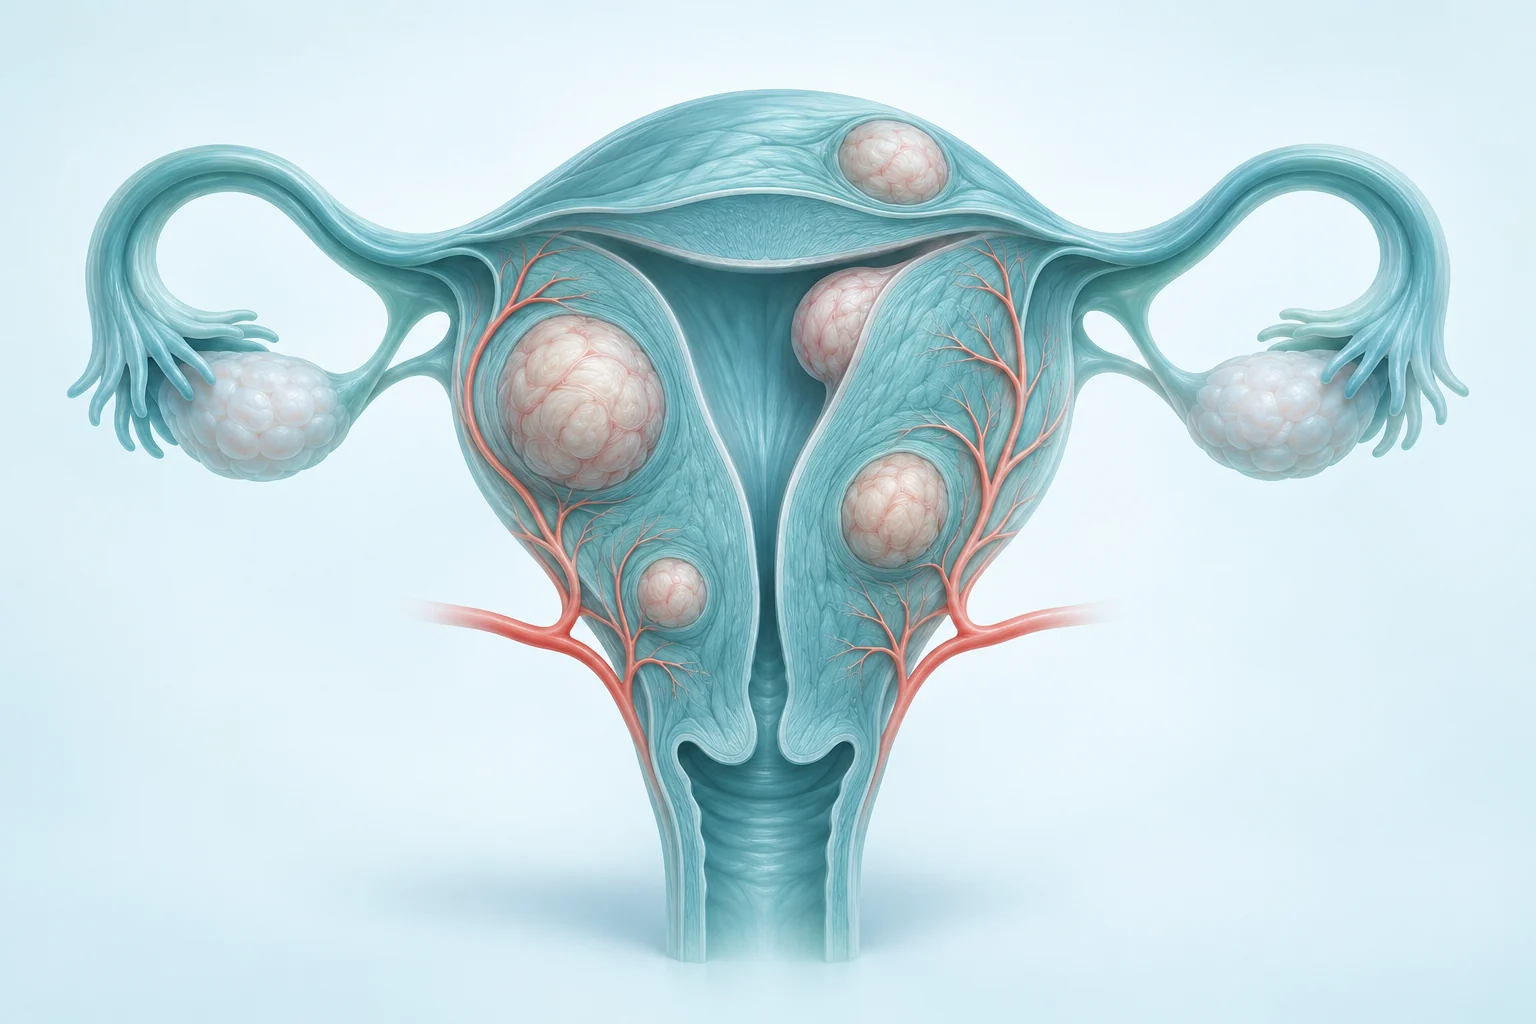
Evaluation focuses on symptomatic fibroids, their location and size, and whether they explain the bleeding or pressure. A scan alone is not enough to select treatment.
Tell the team whether you hope to conceive, may want pregnancy later or are unsure. Uterus preservation and fertility outcomes are different questions that require specific counseling.
Pregnancy, active pelvic infection or concern for malignancy can change or rule out the plan. Kidney function, contrast allergy, bleeding risk and other health conditions also matter.
A gynecologist and interventional radiologist can help compare options. If future pregnancy is a priority, discuss whether myomectomy or further fertility evaluation is more appropriate before committing to UFE.
| Option | What it does | What to consider |
|---|---|---|
| Observation / medication | Monitoring or medicines may be appropriate for mild symptoms or bleeding control. | Effect on bulk symptoms, duration of use and reproductive goals vary by treatment. |
| UFE / UAE | Reduces fibroid blood supply so treated fibroids can shrink. | Keeps the uterus; cramping and fatigue are expected early. Symptoms may persist or recur. |
| Myomectomy | Surgically removes fibroids while retaining the uterus. | Route depends on fibroid location, size and number. Discuss scarring, recurrence and pregnancy plans. |
| Hysterectomy | Removes the uterus and provides definitive treatment for uterine fibroids. | Pregnancy is no longer possible. Surgical route and medical factors influence recovery and risks. |
Recovery comparisons should use the specific surgery proposed. Hysteroscopic, laparoscopic and open abdominal procedures have different experiences and timelines.
The FEMME randomized trial found improved fibroid-related quality of life after both UAE and myomectomy. Myomectomy had the larger average improvement at two years. At four years, the estimated difference still favored myomectomy but was not statistically significant; missing follow-up data limited certainty.
The four-year report recorded more repeat procedures after UAE than after myomectomy, with an imprecise estimate. Initial recovery and the possibility of further treatment both belong in a balanced comparison. FEMME trial report; four-year follow-up.
What about future pregnancy? Pregnancies have occurred after both procedures, but the FEMME pregnancy numbers were too small to establish which treatment provides better reproductive outcomes. Neither uterus preservation nor a single reported pregnancy proves equivalent fertility or pregnancy safety. Read the reproductive-outcomes analysis.
Bring imaging reports, bleeding history, anemia testing if available and previous treatment records. Ask whether additional gynecologic evaluation is needed.
Discuss the arterial access site, sedation, pain-control plan, medicines and whether an overnight stay may be appropriate. Arrange transportation and support for early recovery.
Using X-ray guidance and contrast, an interventional radiologist advances a catheter to the uterine arteries and delivers embolic particles to reduce fibroid blood flow.
ACR/RSNA’s UFE patient guide describes procedure preparation and what happens afterward.
Pelvic cramping, fatigue, nausea and other post-embolization symptoms can occur early. Pain management and clear after-hours contact instructions are important. Some patients leave the same day; others need observation or an overnight stay.
Many patients return to usual activities in about one to two weeks, but recovery depends on symptoms, work demands and the treatment course. Fibroid shrinkage and relief of pressure symptoms develop over months. Follow the team’s instructions rather than treating a typical timeline as a personal deadline.
Follow-up assesses bleeding, pressure symptoms and whether further imaging or treatment is needed. Persistent, recurrent or changing symptoms deserve review.
Potential risks include arterial-access bleeding, infection, contrast reaction, radiation exposure and unintended embolization. Fibroid tissue can sometimes pass through the cervix. Changes in ovarian function or menstrual periods can occur, and persistent symptoms or complications may require another procedure, including surgery. Johns Hopkins’ UAE overview describes risks to discuss.
Seek urgent assessment for severe or worsening pelvic pain, fever that persists or develops with worsening symptoms, foul-smelling discharge, heavy bleeding with faintness, or other concerning symptoms after treatment. Heavy bleeding with dizziness, fainting or shortness of breath also needs prompt care before any elective consultation.
Meet with Nathanael Sabbah, MD to discuss your diagnosis, previous treatment and goals. Our consultation locations serve patients across the San Fernando Valley and Orange County. Confirm the consultation address and procedure facility when scheduling; they may be different.
15211 Vanowen Street, Suite 305, Van Nuys, CA 91405. View Van Nuys office
18370 Burbank Boulevard, Suite 514, Tarzana, CA 91356. View Tarzana office
10900 Warner Avenue, Suite 101A, Fountain Valley, CA 92708. View Fountain Valley office
Who performs embolization? An interventional radiologist evaluates and treats the relevant arteries using imaging guidance. Dr. Sabbah’s Cedars-Sinai provider profile lists his training and board certifications. Your consultation should cover the planned technique, alternatives, risks and follow-up—not just the procedure name.
Coverage and out-of-pocket cost depend on the specific plan, medical-necessity criteria, authorization, clinician and facility. An office accepting an insurance plan does not establish that the procedure is covered. Ask for verification and an estimate before scheduling treatment.
Bring imaging reports, your medication and allergy lists, previous procedure records and your main questions. Do not stop prescribed medicines without instructions from your treating team.
For fibroid treatment, UFE and UAE commonly refer to the same embolization approach. UAE is a broader term that can also describe embolization for other uterine conditions; the reason for the procedure should be clear.
No. UFE reduces their blood supply so treated fibroids can shrink. Myomectomy removes fibroids surgically. Either approach can leave a need for additional care if symptoms persist or recur.
Pregnancy can occur, but UFE does not guarantee preserved fertility or equivalent pregnancy outcomes to other treatments. Discuss your goals with gynecology and interventional radiology before treatment, including whether myomectomy or fertility evaluation is more appropriate.
Many patients resume usual activities in approximately one to two weeks, although cramping, fatigue, work demands and individual recovery can change that timeline. Follow your treating team’s instructions for driving, lifting, exercise and return to work.
Improvement develops over time and varies by symptom and patient. Fibroid shrinkage and pressure relief generally evolve over months. Follow-up is needed to assess bleeding, bulk symptoms and whether additional treatment is required.
Neither is best for everyone. Symptoms, fibroid location, pregnancy goals, the proposed surgical route and the evidence on quality of life and repeat treatment should guide a shared decision.
Symptoms may persist or recur and further treatment can be necessary. Follow-up should reassess the cause of symptoms rather than assuming every new symptom is from the same fibroid.
Coverage, authorization and out-of-pocket cost depend on your plan and the proposed clinician and facility. Ask for procedure-specific verification and a written estimate before scheduling.
SoCal Interventional offers UFE evaluations in Van Nuys, Tarzana and Fountain Valley. Call (310) 929-0026 or use the appointment form for a nonurgent request; confirm the consultation and procedure locations.
Editorially updated November 4, 2026. Prepared by the SoCal Interventional Editorial Team using the clinical sources linked on this page. Educational information does not replace an individual medical evaluation. Read our editorial policy.
Use the appointment form below for a nonurgent consultation, or call (310) 929-0026.
Physician information: Nathanael Sabbah, MD, interventional radiologist.
SoCal Interventional Encino
16250 Ventura Blvd, Suite 160, Encino, CA 91436
PAE, GAE and UFE consultations are planned. Hours from opening: Monday–Friday, 8:00 AM–5:00 PM. This office is not yet open; Tarzana, Van Nuys and Fountain Valley remain available. Confirm the address for each appointment; your procedure facility may differ.
Encino office details · (310) 929-0026 · Ask about appointment availability