Symptoms that matter
Bothersome urinary symptoms despite medication, medication side effects or a preference to discuss procedural options may prompt evaluation. The severity of symptoms alone does not establish eligibility.
Los Angeles & Orange County · PAE care
A catheter-based option for enlarged-prostate symptoms. Understand whether PAE fits your urinary symptoms, anatomy and priorities before choosing treatment.
Van Nuys · Tarzana · Fountain Valley
Waking repeatedly at night? Read our nocturia guide to understand when BPH may be the cause.
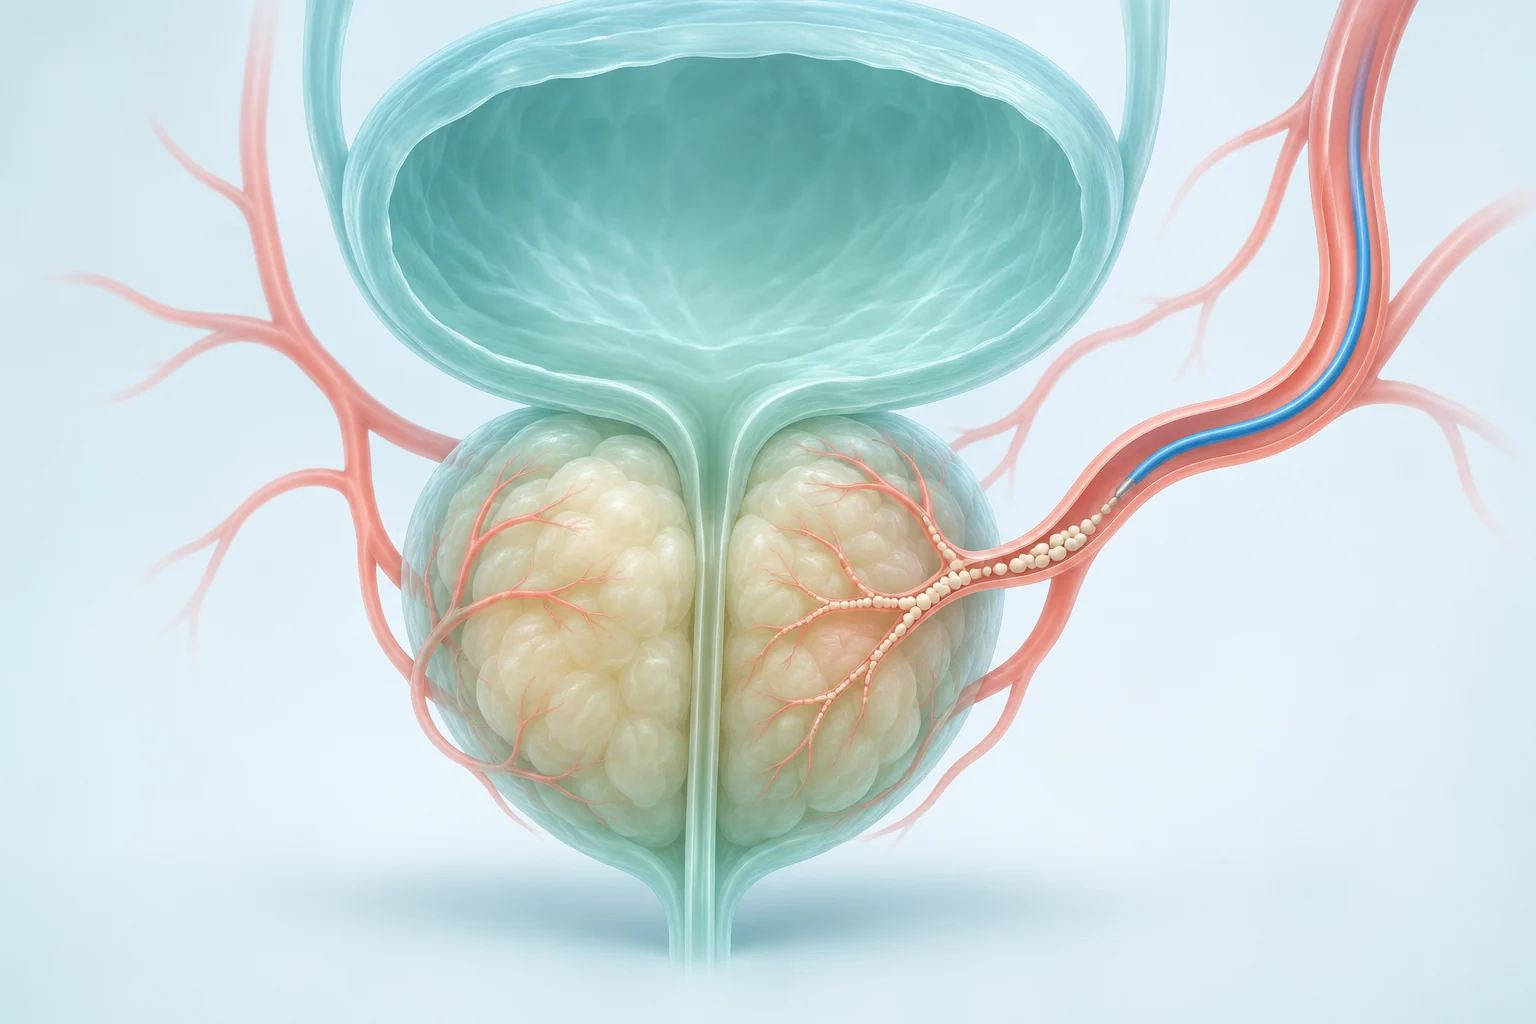
Can PAE treat an enlarged prostate without prostate surgery? PAE reduces blood flow to selected prostate tissue through a small arterial catheter. As treated tissue shrinks, urinary symptoms from benign prostatic hyperplasia (BPH) may improve. It avoids removing prostate tissue through the urethra, but it still has procedural risks and does not work equally well for everyone.
Weak stream, difficulty starting, urgency, frequent urination and waking at night can occur with BPH. Bladder conditions, infection, urethral narrowing, medications and other causes can produce similar symptoms. PAE is considered after establishing the cause; it is not a treatment for prostate cancer.
The interventional radiologist uses X-ray imaging and contrast to guide a catheter from an artery in the wrist or groin to selected prostate arteries. Embolic particles reduce blood flow. Access, sedation and discharge plans depend on the individual case.
Explore the full BPH treatment overview
Bothersome urinary symptoms despite medication, medication side effects or a preference to discuss procedural options may prompt evaluation. The severity of symptoms alone does not establish eligibility.
Review may include a symptom score, prostate imaging or volume, PSA when appropriate, urine testing, bladder emptying and flow assessment. Urologic evaluation may be needed to assess obstruction or another diagnosis.
Arterial anatomy, kidney function, contrast allergy, bleeding risk and overall health affect suitability. Urinary retention requires assessment of its cause and bladder function; catheter removal cannot be guaranteed.
The 2026 AUA guideline gives PAE a conditional recommendation in appropriately selected patients, with strongest evidence in prostates of at least 50 mL. SIR guidance allows individualized consideration in some smaller glands. Size is one part of selection, not an automatic qualification. AUA procedural guideline; SIR practice guidance.
| Option | What it does | What to consider |
|---|---|---|
| Medication | May relax the outlet or reduce prostate volume, depending on the drug. | Benefits, side effects, ongoing use and complications of obstruction should be reviewed. |
| PAE | Reduces blood supply to selected prostate tissue without transurethral tissue removal. | Improvement is gradual; incomplete response or another treatment is possible. |
| TURP / HoLEP | Remove obstructing tissue through the urethra. | Often provide stronger relief of obstruction; anesthesia, bleeding, recovery and sexual effects vary. |
| UroLift / Rezūm / Aquablation | Use different techniques to open the urinary channel or treat tissue. | Prostate size and anatomy, durability, ejaculation priorities and recovery influence selection. |
Erectile and ejaculatory function are often preserved after PAE, but no sexual outcome can be guaranteed. Compare the actual procedures offered to you with both interventional radiology and urology.
A randomized sham-controlled trial supports symptom benefit from PAE in selected patients. In a separate five-year randomized comparison, both PAE and TURP improved symptoms, while TURP generally produced stronger objective improvements in urinary flow and obstruction measures. The procedures have different tradeoffs; PAE should not be presented as equivalent to surgery for every outcome.
PAE sham-controlled trial · Five-year PAE vs TURP trial.
How long does PAE last? Benefit can persist for years in responders, but symptoms may remain or recur. Prostate growth, bladder function and other conditions can change the result. Follow-up should assess symptom scores, bladder emptying and whether additional treatment is needed.
Observation follows the procedure. The care team checks the access site, comfort and ability to urinate and provides a discharge or overnight-care plan.
Pelvic discomfort, burning, frequency or a temporary increase in urinary symptoms can occur. Follow individualized instructions for medicines, lifting, driving, work and catheter care if applicable.
Symptom improvement is usually assessed over weeks to months rather than immediately. Keep follow-up appointments even if symptoms improve, and discuss persistent or worsening problems.
Potential risks include access-site bleeding or bruising, temporary urinary symptoms or retention, infection, contrast reaction, kidney injury and radiation exposure. Rare unintended embolization can injure nearby tissue. The physician should explain your particular risks and how they are managed.
Seek prompt medical care for inability to urinate, fever with urinary symptoms, significant blood or clots in the urine, or severe worsening pain. After a procedure, follow the team’s urgent-contact instructions. An appointment form is not an emergency service.
Meet with Nathanael Sabbah, MD to discuss your diagnosis, previous treatment and goals. Our consultation locations serve patients across the San Fernando Valley and Orange County. Confirm the consultation address and procedure facility when scheduling; they may be different.
15211 Vanowen Street, Suite 305, Van Nuys, CA 91405. View Van Nuys office
18370 Burbank Boulevard, Suite 514, Tarzana, CA 91356. View Tarzana office
10900 Warner Avenue, Suite 101A, Fountain Valley, CA 92708. View Fountain Valley office
Who performs embolization? An interventional radiologist evaluates and treats the relevant arteries using imaging guidance. Dr. Sabbah’s Cedars-Sinai provider profile lists his training and board certifications. Your consultation should cover the planned technique, alternatives, risks and follow-up—not just the procedure name.
Coverage and out-of-pocket cost depend on the specific plan, medical-necessity criteria, authorization, clinician and facility. An office accepting an insurance plan does not establish that the procedure is covered. Ask for verification and an estimate before scheduling treatment.
Bring imaging reports, your medication and allergy lists, previous procedure records and your main questions. Do not stop prescribed medicines without instructions from your treating team.
PAE is a minimally invasive arterial catheter procedure. It does not remove prostate tissue through the urethra, but it still requires an assessment, image guidance, appropriate sedation or anesthesia planning, and discussion of procedural risks.
An interventional radiologist performs PAE. Evaluation may also involve a urologist to confirm the cause of urinary symptoms, assess obstruction and compare treatments.
Improvement, when it occurs, is usually assessed over weeks to months. Symptoms can temporarily worsen early after treatment. Some patients have limited benefit or need additional care.
PAE is an alternative for selected patients, not an equivalent substitute for every situation. Tissue-removing procedures may provide stronger relief of obstruction. Anatomy, bladder function, medical risk and patient priorities guide the discussion.
Erectile and ejaculatory function are often preserved, but no sexual outcome can be guaranteed. Discuss your baseline function and priorities along with the risks of each treatment.
Some patients with retention may be evaluated, but the cause of retention and bladder function must be assessed. PAE does not guarantee catheter removal, and another approach may be more appropriate.
Coverage depends on the plan, clinical criteria, authorization and the treating facility and clinician. Ask for procedure-specific verification and a cost estimate before scheduling.
SoCal Interventional offers PAE consultations in Van Nuys, Tarzana and Fountain Valley. Call (310) 929-0026 or use the appointment form. Confirm your consultation address and procedure location when scheduling.
Editorially updated November 4, 2026. Prepared by the SoCal Interventional Editorial Team using the clinical sources linked on this page. Educational information does not replace an individual medical evaluation. Read our editorial policy.
Use the appointment form below for a nonurgent consultation, or call (310) 929-0026.
Physician information: Nathanael Sabbah, MD, interventional radiologist.
SoCal Interventional Encino
16250 Ventura Blvd, Suite 160, Encino, CA 91436
PAE, GAE and UFE consultations are planned. Hours from opening: Monday–Friday, 8:00 AM–5:00 PM. This office is not yet open; Tarzana, Van Nuys and Fountain Valley remain available. Confirm the address for each appointment; your procedure facility may differ.
Encino office details · (310) 929-0026 · Ask about appointment availability